AI
Swiss researchers use retinal images to estimate biological age
A University of Lausanne-led team has developed an AI model that estimates biological age from retinal photographs. The article would explain how the model was trained on more than 70,000 people, what an age gap may reveal about risks including cardiovascular disease, cancer and dementia, and the limits of using retinal age as a medical screening tool.
Lausanne AI reads biological age in the eye
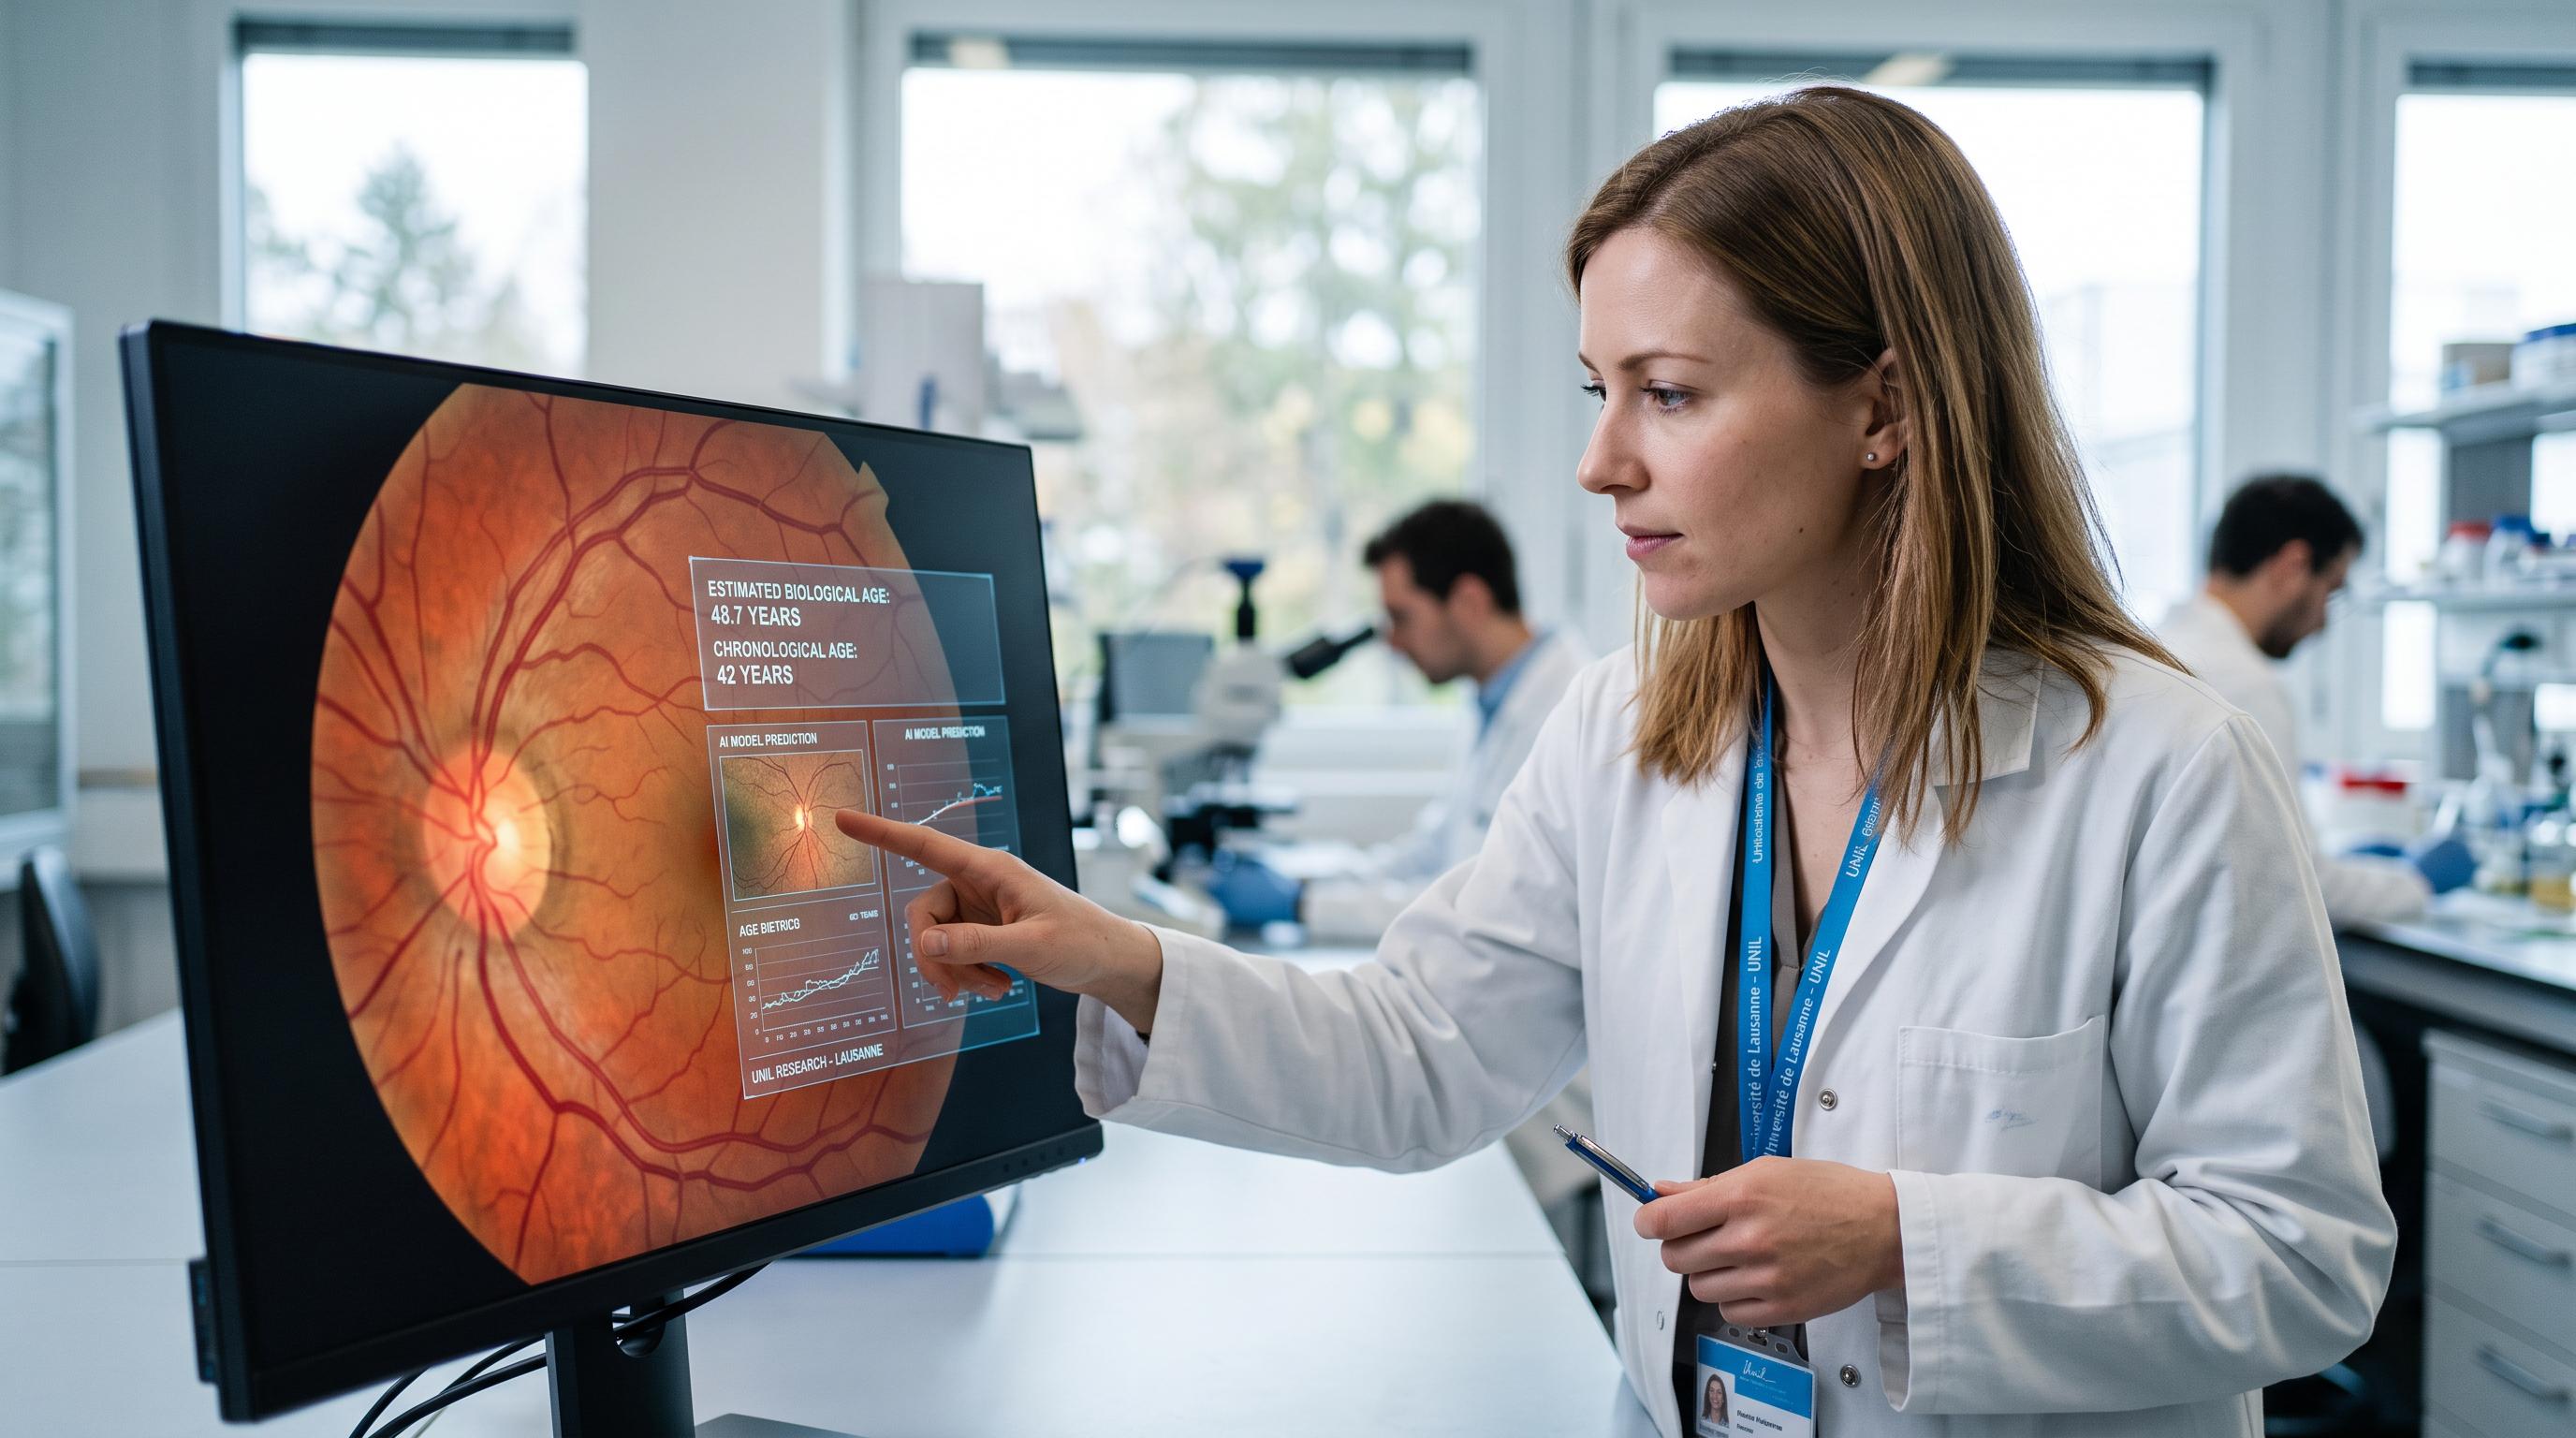
More than 70,000 retinal images helped a University of Lausanne-led team build an artificial intelligence system that estimates biological age from a photograph of the eye. The findings, published in Nature Communications and reported on September 16, 2026, point to a new way of studying health risks through a routine ophthalmic image.
The model estimates how old a person’s retina appears, then compares that figure with their chronological age. An average difference of less than three years shows that the system can make a close age estimate across the study population, which included adults aged 40 to 79.
The research matters because the retina contains a dense network of blood vessels and nerve tissue that can reflect changes elsewhere in the body. The AI detects subtle differences in colour, brightness and vessel density that may be difficult for a human observer to identify.
For Swiss patients, the prospect is significant, particularly as retinal photographs are already used in eye care. Yet the model remains a research tool. A retina that appears older may signal elevated risk, but it cannot diagnose cancer, dementia or cardiovascular disease on its own.
The age gap may reveal hidden health risks
A retinal age gap can act as a health warning sign. The study found that people whose retinas appeared older than their actual age faced stronger associations with cardiovascular and respiratory disease, cancer and dementia.
That finding does not mean the algorithm can predict an individual diagnosis. The researchers observed statistical links across a large population, rather than proving that accelerated retinal ageing causes any particular illness. A higher retinal age could reflect several influences, including existing health conditions, smoking or vascular damage.
The distinction is essential for any future use in Swiss medical practice. A screening result could encourage a patient to seek follow-up checks for blood pressure, diabetes or other established risk factors. It should not replace a doctor’s examination, laboratory tests or imaging designed for a specific disease.
The promise lies in combining the retinal estimate with established clinical information. A general practitioner or ophthalmologist could potentially use an unusual age gap as one signal among many. Researchers still need to test how reliably the model works in different populations and whether acting on its results improves outcomes.
Sex and menopause change the picture
Men and women showed different retinal-age patterns. In men, an older-looking retina was more strongly associated with characteristics of metabolic syndrome, including high blood pressure, diabetes and being overweight.
Women showed a stronger relationship between retinal age and vascular factors, including an increased risk of thrombosis. The study also identified a change around menopause. Before menopause, women’s retinas appeared younger on average than men’s. After menopause, that difference was reversed.
The researchers did not establish that hormonal changes caused the shift. The result does, however, raise questions about how sex, age and vascular health interact in the retina. Those questions matter for medical research because risk profiles are not identical across populations.
The findings also caution against treating biological age as a single, universal measure. An algorithm may detect patterns that vary by sex, age group or health background. Before clinicians use such a score, independent studies will need to assess whether it remains accurate for people outside the original dataset, including different ethnic groups and patients with varied medical histories.
Smoking points to prevention, not certainty
Smoking was the strongest factor linked to accelerated retinal ageing. The association adds to evidence that the retina can reflect damage connected to circulation and long-term lifestyle exposure. The study also points to early treatment of cardiovascular problems as a possible way to reduce risk, although it does not show that changing one factor will make a retina appear younger.
The potential public health use is straightforward. Retinal photographs are quick to obtain, and AI could help identify people who need closer attention to blood pressure, diabetes, smoking or vascular health. In Switzerland, such a tool might eventually support prevention in general practices, hospitals or ophthalmology services.
Several barriers remain. The model needs validation in new groups and clinical settings. Researchers must determine how often it produces false alarms, whether results vary between imaging devices and how doctors should interpret an age gap. Patients would also need clear information about what the score can and cannot say.
Privacy will require careful handling. Retinal images are health data, and any Swiss deployment would need strong safeguards for storage, access and secondary use. Technical accuracy alone will not decide whether the system belongs in routine care.
Researchers face the clinical test
The Lausanne system is closer to a research signal than a finished screening test. Its performance in a large dataset is encouraging, but an average error of less than three years does not explain every person’s result. The estimate describes how old a retina looks to the algorithm, not the full biological condition of the patient.
Further research will need to establish whether the model predicts future illness better than existing risk scores. Studies should also examine people from a wider range of backgrounds, medical conditions and healthcare settings. Images taken with different cameras may produce different results, and algorithms can inherit biases from the data used to train them.
For now, Swiss doctors would still need to interpret any retinal-age result alongside symptoms, medical history and standard tests. Patients should not regard an older estimate as proof that cancer, dementia or heart disease is present, nor should a younger estimate be treated as a guarantee of good health.
The University of Lausanne study gives researchers a practical way to investigate ageing through the eye. Its next test will be clinical: whether the measurement can guide prevention accurately, fairly and safely enough to improve care.